The ruling elite typically aims to accumulate an immense amount of wealth, which often can only be obtained by extracting it from a large number of people, hence requiring each of those people sacrifices their quality of life to meet the elite’s needs. An excellent meme, in turn, synopsizes the challenge ruling elites seeking this excessive wealth and power have faced throughout history:
Since it is not economically feasible to directly force an entire population into submission (e.g., the estimates I’ve found put 3-5% of the population as the maximum number of soldiers a society can afford to support), a variety of other tactics have been reused throughout history to keep the population compliant. These include:
• Use crises (e.g., war, plague, famine, or financial panic) to justify emergency powers, mute ordinary skepticism, and recast dissent as sabotage. The pattern is ancient: a problem arises, the public demands protection, and the apparatus claiming to provide it expands—all while fear makes the population far easier to divide and control.
• Make public examples of non-compliant individuals so everyone is scared into compliance, or maintain a system for punishing (and monitoring) dissenters that everyone feels is always hanging over their shoulder. This goes hand-in-hand with making the legal and bureaucratic system so complex it can’t be navigated without specialists the system itself trains (raising the cost of challenging it) and that almost everyone is technically in violation of something—which allows the law to be selectively applied so only those who challenge vested interests are arrested or prosecuted.
• Reward compliance, as careers, grants, titles, access, and prestige for those who play along are just as important as the examples made of the defiant (since most people would rather climb the existing hierarchy than tear it down).
• Create a rigid social hierarchy everyone defers to, and then buy out its top (e.g., having a few select “prestigious” medical journals, “impartial” guideline panels, regulatory agencies, or “experts” be deferred to for medical guidance while everything else is ridiculed as “uncredible”—despite each of them typically taking significant pharmaceutical money and only supporting industry narratives).
Note: one major problem in medicine (which is ingrained through numerous compliance mechanisms) is that the majority of doctors are not willing to deviate from standardized protocols and guidelines—even when it is clear they will not produce an acceptable outcome for the patient (instead, in those situations, they will simply insist they did their best and there was “nothing we could do”).
• Structure the system so everyone is forced to work within that hierarchy (e.g., making physician employment, reimbursement, and immunity from lawsuits dependent upon following the “standard of care” and requiring all other healthcare workers to defer their judgement to physicians).
Note: I believe this accounts for the aggressive push to move doctors from independent to corporate practice. For example, Obamacare was structured to facilitate this, as immediately prior to its passage, 60-70% of physicians were in independent or doctor-owned practices,1,2,3 whereas by 2024, only 35-42% were1,2 (e.g., a 2024 article was titled “Doctors continue to shift away from private practice, citing insurer payment rates and regulatory issues”).
• Make accumulating money be a guiding principle everyone in the society strives for and then use economic incentives (since they can easily be changed from the top down) to create the desired behavior in the population (e.g., Biden’s federal policies leading to most workers being told they would be fired if they didn’t vaccinate).
• Have every media source parrot the same message needed to maintain the status quo (as this persuades most of the population since people like to follow the crowd). This is often paired with well crafted propaganda that effectively misleads the public.
• Create a devout belief in the state or its leader, which not only makes people compliant but also leads them to attack those who aren’t, thereby making the population police itself.
• Create a robust social framework everyone is expected to fit into that requires compliance at each step while simultaneously training people to be compliant (e.g., go to school to go to college to get a job to get married).
• Atomize the population. Independent bases of loyalty (e.g., extended family, church, guild, or town) are much harder to extract from than isolated individuals, so weakening them leaves people facing the state and the market alone—at which point they are far easier to message, hire, saddle with debt, and shame.
• Whenever something awful and unacceptable will be done, first test and refine it on a marginalized group that cannot advocate for itself, and once it succeeds, use that success to normalize it so it can be done to the general population. This is why I feel it’s critical not to ignore it when this happens to others, as beyond that apathy being immoral, it often sets people up to be subjected to the same thing once it has gained so much momentum it can no longer be easily opposed (best synopsized by the famous Holocaust poem where the speaker did not speak up for each successive group targeted because he did not belong to it, which concludes with “Then they came for me, And there was no one left To speak out for me”).
Note: pages could be written about how this applies across the medical field (e.g., prior to COVID, one of my longstanding frustrations was helping people who’d been severely injured by a pharmaceutical that never should have been in general use, as despite the immense suffering, no one really cared because not enough people were affected). Likewise, I’ve recently been thinking about the broader implications of the Ukrainian government’s decision to sacrifice its population and country to keep the war going so they can continue enriching themselves from it.
• Normalize and gradually increase the exploitation so people view it as a fact of life rather than noticing (let alone questioning) it. For example, since the medical system is structured to continually produce costly proprietary drugs patients must take for long periods (if not permanently), treatments which compete with this model are suppressed. When DMSO was discovered in the 1960s, it was better than any existing therapy for many illnesses, yet it was dismissed for “insufficient evidence” compared to “proven cures” (many of which were later pulled from the market), and it remained suppressed despite tens of thousands of studies showing its utility and foreign healthcare systems (e.g., Russia and Ukraine) adopting it. Most importantly, when I drew interest back to it sixty years later, it was still more effective than any approved therapy for many ailments (which is why that series got so much traction). A major reason I’ve put so much work into it, in turn, was to show that the primary obstacle to solving many of the illnesses we face is the structure of the medical system itself.
Note: I think one of the major mistakes the ruling class has made recently, in the pursuit of further profit, was to escalate the exploitation so rapidly that the public is now noticing it.
• Distract and preoccupy the populace so they don’t focus on the major issues facing them (e.g., with “bread and circuses” or by dividing them so they blame another segment of society rather than the ruling class actually creating their problems).
Note: one of my major fears about AI is that it effectively solves the problem elites have struggled with for centuries (being able to afford enough soldiers to police the population), since AI is much cheaper than a full time soldier and hence makes it feasible to exert a much greater degree of control over each member of the population.
The COVID-19 Pandemic
Since people are uncreative, the above playbook also explains exactly what happened during COVID.
In my own case, through internet posts, I believe I became aware of a problematic coronavirus circulating in China in late December (based on checking my calendars I think it was around December 19th, but when I looked up the timeline it appeared on the internet around December 31st). I subscribe to the view that pandemics are almost always massively hyped up to support the biopreparedness industry (detailed here), but in this case, I instead broke from my preconceived biases and became increasingly concerned about this virus as:
• It seemed to be quite dangerous and highly transmissible
• It seemed highly likely it was an lab-made weaponized pathogen.
• Despite more and more signs accumulating that it was the deadly pandemic the industry had been waiting decades for, rather than hype it up, the media (and the Democrat party) continually downplayed its significance and attacked those who raised concerns about it—even once it had spread to Europe and created a similar wave of problems to what was seen in China.
Given what Fauci and the health system had done to the (marginalized at the time) gay community during AIDS (where as much fear as possible was generated about the virus while everything that worked was suppressed, and a toxic and ineffective drug was pushed through despite public and Congressional pushback), I assumed Fauci and those behind him would do the same thing during COVID. As such, my sense was that if I did not find a way to treat this illness (as I had no faith the medical system would), people I knew were going to die, and likewise, if an effective cure could not be adopted, a lot of really bad stuff was going to happen (most of which subsequently did).
Note: I initially thought COVID would be an issue for about a year before it mutated to a much more benign variant (as this is what always happens), but once I saw how measures were being taken to prevent the population from developing herd immunity to protect the market for the vaccine (which was later admitted by HHS officials), I realized this would drag on far longer, particularly since the design of the vaccines also prevented the population from developing herd immunity.
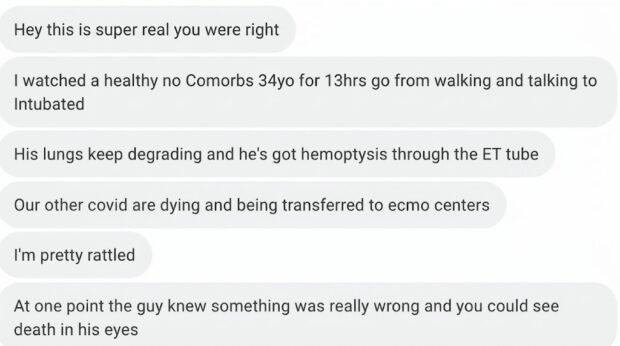
Because of this, in the months leading up to COVID hitting America, in addition to looking down every alley I could for a viable solution to COVID, I tried to alert my colleagues to the problem we were facing (almost none of whom believed me) until eventually, in the middle of March, one working in NYC sent me this text (along with many more describing the catastrophe they were facing and the climate of fear there):
Note: one of the most common debates about COVID was if “it really mattered.” My own assessment is that the original variants (that many did not see) were much more dangerous than the later ones, individual susceptivity greatly varied, it only hit certain areas really badly (I still don’t know why this is, but my best guesses are either that harmful variants were seeded there or a collective fear in the area worsened the disease), and that as time went on and the industry had established itself but the virus became less dangerous, more and more things were done to justify the industry perpetuating itself (e.g., relabeling flus or automobile injuries as COVID and using harmful hospital protocols to significantly inflate the death rate). As such, depending on which part of that picture you focused on, COVID could appear to be extremely dangerous or completely harmless.
Likewise, once the pandemic started, I was inherently skeptical of sending people to hospitals, as:
• While hospitals are excellent at addressing many serious ailments, they often fare poorly with viral disease (as most effective antiviral therapies are not patentable and hence rejected by medicine).
• Hospitals are very quick to give up on patients and say “nothing can be done.”
• Hospitals are highly resistant to allowing people to try alternative therapies, even when everyone agrees that patient will die and nothing can be done (which had led to more cases than I can count of people being snuck alternative therapies in the hospital and then “miraculously” recovering).
• There was a climate of fear amongst medical professionals (as for the first time in their careers, they felt they were in danger too) so they wanted to minimize their interactions with patients as much as possible (which would lead to even worse care). Likewise, I was expecting below average care because the hospital systems were overwhelmed and locked into a triage mindset.
Note: generally, these issues tend to be much worse with large “prestigious” hospitals than small rural ones (which mirrored what I saw during the pandemic). For this reason, I previously wrote an article on the dangers of hospital care and how one can best navigate it here.
Likewise, I was also alarmed by two federal policies (that were likely shaped by lobbyists):
• First, to combat COVID, a series of (well-intentioned) policies were enacted, such as the government covering COVID hospitalizations for the uninsured (incentivizing hospitals to admit more “COVID” patients and diagnose admitted patients with COVID), shielding healthcare providers from malpractice when treating COVID (thereby incentivizing poorer care and the use of unsafe countermeasures), and the Trump administration doing all they could to secure ample ventilators for America (which incentivized ventilating patients who weren’t good candidates for ventilators and needing people without adequate ventilator training being needed to operate many of them—both of which increased mortality).
Note: one of the least appreciated facts about COVID was that since the spike protein (through disrupting zeta potential) caused microclotting throughout the body (which disproportionately affects the smallest vessels) blood oxygenation was much poorer in the periphery than the internal organs. Since oxygen saturation is measured in the finger tips, many patients hence had critically low blood oxygenation (which requires intubation) despite them clinically being fine, and since it took a while for the medical field to recognize many of these patients did not need ventilation (and that ventilation often resulted in death), for a prolonged period, many were inappropriately vented and died.
Most importantly, to make up for the money hospitals had lost (because they saw fewer patients for other things due to the lockdowns), grant subsidies were given to make up the shortfall. While these were initially automatic and first based on the previous year’s revenue (and then increased so the total came to about 2% of their net patient revenue), those that followed were allocated to hospitals in high COVID impact areas (hospitals that had higher numbers of COVID admissions), where, in addition to their standard reimbursement billing, hospitals received $76,975 per COVID admission, and then, after 4 months, $50,000 instead (as this policy predictably incentivized more “COVID” admissions—corroborated by a senior HHS official, in a media call stating that the reduced funding is due to the number of such admissions surging from about 50,000 in the first round to more than 400,000 by the time of the second round1). Likewise, the March 27 CARES Act required Medicare to increase reimbursement for COVID hospitalizations by 20%.1
Note: prior to COVID, Medicare’s average payment for someone hospitalized for a respiratory infection was $13,297, $17,437 if they were also vented for less than 4 days, and $40,218 if vented for over 4 days, so venting patients long-term effectively tripled the reimbursement (before the 20% add-on was included).1
•Second near the start of the pandemic (4/29/2020) Fauci announced to the world that the antiviral remdesivir would be the standard of care for COVID, not unlike how he’d made the antiviral AZT be the standard of care for AIDS (despite minimal evidence of efficacy, and significant evidence showing it made AIDS worse). Beyond the AZT parallels, it was also a red flag that remdesivir was a non-specific antiviral that needed a home (as it had not worked for Ebola) rather than a therapy specific to COVID, that the existing data for remdesivir was very poor (Fauci even cited fairly lackluster benefits to justify it being the standard of care), and that like AZT, safety concerns existed with the drug.
Note: in contrast to remdesivir, the monoclonal antibodies were new drugs that were specific to COVID, and in turn, they actually worked quite well (which not surprisingly led to their access being increasingly restricted, as being able to treat COVID disrupted the existing business model.
Because of Fauci’s pronouncement, I felt hospitals would aggressively push remdesivir protocols as following the standard of care significantly shielded them from liability. More importantly, in November 2020, Medicare created the New COVID-19 Treatments Add-on Payment (NCTAP) to ‘mitigate potential financial disincentives’ for hospitals to use remdesivir, which paid hospitals 65% of whatever a COVID stay cost beyond the standard Medicare payment (capped at 65% of the outlier threshold)1,2—but only if remdesivir or a small number of other drugs was billed on the claim (and the code could be used even if the hospital got the drug for free)1. In turn, giving remdesivir to a patient headed for a long ICU stay meant Medicare would cover most of the losses that would otherwise come out of the hospital’s pocket, and the sicker the patient became (which remdesivir’s toxicity helped bring about), the more that code was worth. This was a huge deal, as normally a hospital had to absorb the first $29,064 of losses on an expensive Medicare case before outlier payments kicked in,1so for each remdesivir patient, this returned up to roughly $19,000 the hospital would have otherwise lost—making it a done decision virtually every hospital would push for every patient to get it to shield them from the massive potential loss they faced from the more costly patients (which is normally counterbalanced by the profitable ones). Likewise, replacing remdesivir with something like ivermectin removed the code that triggered the payment, so it was actually fiscally worth it for hospitals to go to court to stop its administration.
Note: in contrast to remdesivir, the monoclonal antibodies were new drugs made specifically for COVID, and in turn, they actually worked quite well (which not surprisingly led to their access being increasingly restricted, as being able to treat COVID disrupted the existing business model).
Because of Fauci’s pronouncement, I felt hospitals would aggressively push remdesivir protocols as following the standard of care significantly shielded them from liability, particularly since insurance subsidies were likely (and in November Medicare even created a separate add-on for costly new COVID drugs such as remdesivir, to ‘mitigate potential financial disincentives,’ which made hospitals less likely to lose money when administering them to an expensive inpatient1).
The post How Hospitals Turned on Their Patients During COVID appeared first on LewRockwell.
0 comments on “How Hospitals Turned on Their Patients During COVID” Add yours →